

A year ago today, then-head of DOGE Elon Musk tweeted, “We spent the weekend feeding USAID into the wood chipper. Could gone to some great parties. Did that instead.”
It was an act that killed people. According to a leading mathematical model, 800,000 people have died who otherwise wouldn’t have due to the (illegal) shuttering of the US Agency for International Development and the cancellation of 83% of its programs. It is as if every single person in North Dakota had died over the last year—that is, if two-thirds of North Dakota were children.
We don’t know most of these people’s names. But thanks to the essential work of journalists, we know some of them. Reporters have identified at least 27 people—mostly children—who very likely would still be here if the Trump administration had not cut off the means of their survival overnight. Much in the way we are remembering Renee Good and Alex Pretti, I think we should also remember these lives taken by the cruel men who lead us.
These deaths were utterly foreseeable. Musk’s wood chipper tweet came after a two week-period that had thrown USAID into chaos. The day Trump took office, the administration announced a 90-day review of USAID programs. Four days later, they ordered them all to suspend work. At that point, there was still hope that it was a temporary adjustment period—that Musk, Trump, and Rubio did not actually intend to terminate a complex global operation working in over 100 countries, including many of the world’s most severe humanitarian emergencies.
But by this time one year ago, it became clear that they did. USAID’s cost amounted to less than 1% of the budget, but the Trump administration still saw this as intolerably high. They didn’t think the richest country in the world should share even a miniscule portion of its bounty, and they saw this as such an urgent problem that USAID needed to be immediately shut down. It was an act so extreme even Project 2025 did not contemplate it.
International aid and development really are complex, and discussions about how to improve them are legitimate and worthwhile. But some things are bracingly simple. If you cut off food and medicine and shelter to some of the poorest and most vulnerable people in the world—without any warning, without giving their governments and other potential donors any time to prepare—people will die.
I hope that remembering those we lost will remind us to protect those who remain. On our current course, we will lose millions more. A study in the medical journal The Lancet found that USAID’s destruction could result in as many as 14 million deaths by 2030. If every day I published an article like this one—remembering 27 people killed by the destruction of USAID—it would take me 1400 years to mourn them all.
Suza Kenyaba

Suza Kenyaba “liked pretty dresses,” but in the one photo we have of her, the Congolese 5-year-old wore a “Happy Halloween” shirt. As malaria ravaged her body, medicine that could have cured her was just seven miles away. The US government had already paid for it and shipped it to a nearby warehouse. But because of the Trump administration’s aid freeze, it hadn’t made it to the health clinic where Suza lay. She died on February 19, 2025.
Reporting: Meg Kelly, Joyce Sohyun Lee, Rael Ombuor, Sarah Blaskey, Andrew Ba Tran, Artur Galocha, Eric Lau, and Katharine Houreld for the Washington Post
Santina

In Kakuma Refugee Camp in Kenya, Mary Sunday rushed her seven-month-old baby Santina to the hospital. Sunday’s mother had died when she was young, and she “considered parenthood a sacred responsibility.” A month before they went to the hospital, US funding cuts had forced the World Food Program to cut rations to 630 calories of rice and lentils per person per day.
Only able to eat one meal a day, Sunday could not produce enough milk to feed Santina. By the time Santina got to the hospital, the baby had sunken eyes and weighed just 11 pounds. The hospital tried everything, but Santina died early on the morning of July 21, 2025. A doctor and nutrition specialist said that it was almost certainly the result of the malnutrition. Sunday felt ashamed. “I felt I wasn’t mother enough,” she said.
Just three days before Santina’s death, visiting Trump administration officials had attended a dinner at their luxury hotel in Nairobi, Kenya. They were traveling to six cities to conduct exit interviews with USAID staff. The Trump administration officials flew business class, and one of them obtained permission to expense $35,000 on the trip, just for himself. The US embassy had already sent eight cables to Marco Rubio’s office to explain the gravity of the situation in Kenya’s refugee camps, and at the dinner USAID staff begged the visiting officials to restore funding.
Standing before the Trump administration officials, a World Food Program staff person showed Tupperware containers displaying the miniscule rations people like Santina’s family were receiving. The officials didn’t express any interest in addressing the crisis. Marcus Thornton, the official who had expensed $35,000 on the trip, “spent much of the meal looking at his cellphone.”
Reporting: Brett Murphy and Anna Maria Barry Jester for ProPublica
Daniella Kalenga

Daniella enjoyed singing in church. She was eight, and she lived in Uganda. When she caught typhoid and malaria, she was unable to access an ambulance or medicines because of USAID funding cuts. Nicholas Kristof asked her mom, Safi Kalenga, what she would say to Americans who thought their government should not pay to support children like Daniella.
Daniella’s mom said, “It’s just a number to you. But my child would be alive today if you could provide just a bit of medicine and food. We’re not helpless. We just need a bit of support, and for want of it we are losing our children. We cannot blame you. But if only you could look at my child as you look at your own child, how would you feel?”
Reporting: Nicholas Kristof for the New York Times
Mohammed Hashim

Before they were starving, Mohammed Hashim had liked playing soccer, but in time he grew weaker and begged his father for food. Part of Myanmar’s persecuted Rohingya minority, the two-year-old lived in an internment camp with his family. The US cut the food aid that the family relied on, forcing the family to go from three meals a day to one. The father Hashim begged for food was himself so weakened that there were days when he couldn’t walk. He couldn’t have gone far anyway—soldiers barred them from leaving the camp. When Hashim died on May 7, his siblings began to scream.
Mohammed Taher, Hashim’s father, says Marco Rubio was lying when he said no one had died because of USAID funding cuts. “I lost my son because of the funding cuts,” he said. “And it is not only me — many more children in other camps have also died helplessly from hunger, malnutrition and no medical treatment.”
Reporting: Kristen Gelineau for the Associated Press
Jane Sunday

Single mother Rovina Naboi, originally from South Sudan, was raising nine children in Kakuma Refugee Camp in Kenya. Her baby Jane Sunday was “playful and full of smiles.” But when US funding cuts led to meagre food rations, Jane fell sick with a fever and chills. Days later, her body began swelling and her skin began to peel and fall off.
Rovina left her other kids alone to take Jane to a clinic seven miles away. A nurse diagnosed her with a severe form of malnutrition—before US funding cuts, they rarely saw such severe cases. Jane’s organs were failing and her skin was losing its ability to protect her from infections and control her temperature. She became hypothermic.
Rovina worried about the kids she had left at home, and after ten days away, her eldest child showed up at the clinic to tell Rovina that they hadn’t eaten in days. “I faced a very difficult situation, thinking of my children dying of hunger,” Rovina said. Children couldn’t be left at the clinic without their parents, and although Jane was improving and supposed to stay in the clinic to continue receiving care, Rovina decided she needed to sneak Jane out and go home. Because funding cuts had left the clinic short staffed, no one noticed.
Rovina walked seven miles home with Jane strapped to her back with a piece of cloth that tore at Jane’s peeling skin. Rovina secured some food for her children and planned to return to the clinic with Jane the next day. But Jane died that morning. “I feel that the heavens have abandoned me,” Rovina said.
Reporting: The New Yorker
Gilbert Kayombo
Gilbert Kayombo was “an energetic” 7-year-old “who loved cars.” He had been diagnosed with HIV, as had the rest of his family—including his father, who had died the year before. Gilbert’s mother made sure he regularly took his medications, and in February 2025, the hospital only gave him a partial refill because they were low on supply from USAID. That supply quickly ran out, and Gilbert’s mother went back to the hospital multiple times to check if they had received more. They hadn’t. The time without medication severely weakened Gilbert’s body, and he fell sick with anemia and malaria. His nurse said he probably would have been able to fight off the sickness if he had been in good health. But he wasn’t. Gilbert died on March 24, 2025.
The Washington Post reported that Gilbert lived in a “neighborhood squeezed between towering mounds of mining waste in Kolwezi,” DR Congo. The area is home to some of the biggest cobalt mines in the world. Cobalt is an essential component in electric vehicles made by Elon Musk’s Tesla.
Reporting: Meg Kelly, Joyce Sohyun Lee, Rael Ombuor, Sarah Blaskey, Andrew Ba Tran, Artur Galocha, Eric Lau, and Katharine Houreld for the Washington Post
Jibia

In fourth grade, Jibia ranked third in her class of 58 students. She hoped to become a nurse. Jibia’s family were Congolese refugees in Uganda, and they had to pull her out of school when the loss of US funding resulted in a mass firing of teachers. “Jibia cried inconsolably” at the news.
Soon after, Jibia fell ill with malaria. At every step in her sickness, USAID funding cuts robbed her of her chance at health. Her malaria could well have been prevented if the bed net she slept under didn’t have holes—aid cuts meant the local health center had run out of nets. Anti-malarial medicines, too, had run out. Her family tried to get her to a hospital, but they struggled to get an ambulance because the drivers had recently been laid off—that too the result of USAID cuts. The malaria had destroyed her red blood cells, and with Uganda’s blood transfusion system struggling after the withdrawal of US support, she couldn’t get one. She died on July 7, 2025.
Jibia’s mom, Valentine Tisifu, said, “It was aid cuts. People are dying every day and night.”
Reporting: Nicholas Kristof for the New York Times
Nyagoa

Nyajime Duop had fled Khartoum, Sudan, with her 1-year-old baby Nyagoa, settling in a remote village in South Sudan. The International Rescue Committee received US funding to provide health services in the area, visiting twice a week and transporting sick people to a nearby clinic.
Nyagoa fell ill with cholera on a day when normally the International Rescue Committee would have visited the village, but they had been forced to suspend operations when the Trump administration cut their funding. Nyagoa died on the Fourth of July.
Reporting: Anna Maria Barry-Jester and Brett Murphy for ProPublica
Nada and Omer

As pro-democracy protesters launched a revolution that eventually brought Omar al-Bashir’s brutal 20-year rule of Sudan to an end, they formed “Emergency Response Rooms” to provide community support. Their success was soon undermined by a military coup, and a civil war began when the coup leaders turned against each other two years later. The Emergency Response Rooms continued with whatever resources they could find, and they received a boost when USAID gave them $12 million, 77% of the initiative’s funding. The family of three-year-old Omer and 18-month-old Nada survived on one meal a day from the Emergency Response Room soup kitchens.
When the Trump administration ordered for work to stop, the kitchens suddenly closed. Nada died first. Their mother Fatma Swak Fadul would walk about “10 hours each day to collect small bundles of firewood she could sell for about a dollar.” But it wasn’t enough to even feed her children boiled wheat. Increasingly malnourished Omer lost his vision. He begged his mother for food. And one night at the end of March 2025, he died.
Reporting: Katharine Houreld and Hafiz Haroun for Washington Post
Jennifer Inyaa and Evan Anzoo
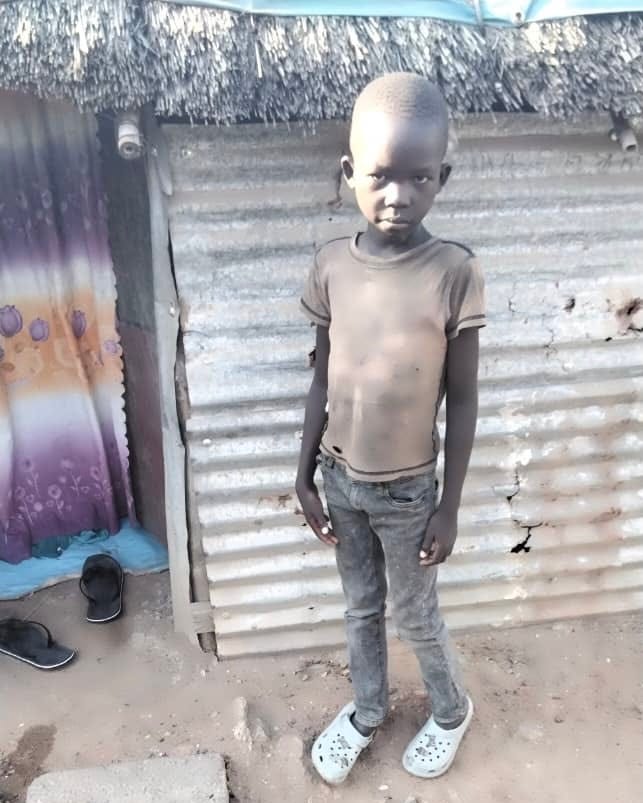
Evan was the 5-year-old son of 35-year-old single mother Jennifer Inyaa. They lived in South Sudan. Both were HIV-positive, and both received medicines from USAID. Soon after that stopped, Jennifer fell sick and died. A week later, Evan died. In May, as Marco Rubio told Congress that no one had died as a result of USAID cuts, Congressman Brad Sherman showed him Evan’s picture. Representative Sherman and Representative Gregory Meeks later introduced the Evan Anzoo Memorial Act that would investigate deaths linked to the dismantling of USAID.
Reporting: Nicholas Kristof for the New York Times
Pe Kha Lau
When 71-year-old Burmese refugee Pe Kha Lau became short of breath—not uncommon, as she had serious lung problems—her son-in-law would carry her to a hospital to receive oxygen. She had been in a US-funded, International Rescue Committee-operated hospital in Thailand when the Trump administration ordered the project to stop work. As a result, Pe Kha Lau was discharged. With the primary source of health care in the area closed, she could not obtain oxygen. She died four days later.
Reporting: Shoon Naing for Reuters
John Abraham
1-year-old John Abraham and his family were refugees in Uganda. They received food aid from the World Food Program, but the US cut funding to the World Food Program and the food aid stopped. John grew weak, and because ambulances were difficult to find after American funding stopped, his seven months pregnant mother Elina Ndacyayisaba “carried John for three hours to a health center.” The health center had run out of supplies to treat John’s severe malnutrition and dehydration, and he died on August 7, 2025.
Reporting: Nicholas Kristof for the New York Times
Peter Donde
Peter Donde was born in South Sudan with HIV. Both his parents died from AIDS. Still just 10, he relied on USAID for his medicines. But this stopped when the Trump administration destroyed USAID. His immune system weakened without the medications, and he died from pneumonia in late February 2025.
Reporting: Nicholas Kristof for the New York Times
Achol Deng
8-year-old Achol Deng was born with HIV, also in South Sudan. Like with Peter, USAID provided her with medications via a case worker. This medicine cost 12 cents per day. Then, Achol lost her ID card and was unable to access medicines without it. Her case worker would have helped her get a new one, but USAID funding had stopped, and she fell sick and died.
Reporting: Nicholas Kristof for the New York Times
Wah K’Ler Paw

Wah K’Ler Paw was a 30-year-old refugee from Myanmar who lived on the Thai-Myanmar border. She received dialysis twice a week at a hospital, but she lost access after the US aid freeze. She hung on for two weeks, and her husband eventually found a way for her to get admitted to receive dialysis at a hospital. It was too late, and she died on February 16, 2025. She had a two-year-old daughter named Thaw Wah.
Reporting: Rebecca Ratcliffe for the Guardian
Abdi Bari
Two-year-old Abdi Bari lived in a camp for displaced people in Somalia—drought and violence had forced his family to leave their hometown around the time of his birth. US-funded support delivered by Mercy Corps allowed him to grow up adequately fed and healthy. The Trump administration cut that funding by 80%. His mother Khadra Hussein Ibrahim was still breastfeeding him, but as she had to travel long distances to search for work and food, she found herself growing weak. Abdi Bari “fell sick with diarrhea and dehydration.” With medical care unavailable in their camp, Abdi Dari’s mother took him five miles to a government-run hospital. When she arrived, “doctors told her it was too late to save him.”
Reporting: Betsy McKay and Caroline Kimeu for the Wall Street Journal
Nyarietna

In a remote region of South Sudan, USAID funding was enabling the Christian nonprofit World Relief to bring a cholera outbreak under control. The funding enabled the purchase of 62 cent IV bags that fought off dehydration, and World Relief’s clinics had successfully treated over 500 people over the previous three months.
In March 2025, Nyarietna began suffering from vomiting and diarrhea. Because the clinic 50 feet from her house had been shut since USAID cut funding, her son Tor Top had to rent a canoe to try to get her to the nearest hospital, eight hours away. Nyarietna died on the way there.
Reporting: Anna Maria Barry-Jester and Brett Murphy for ProPublica
Rebecca Nyariaka

28-year-old Rebecca Nyariaka met Koang Kai in high school and they later married. They fled to Bentiu Refugee Camp in South Sudan after their hometown became too dangerous. Bentiu has effectively been an island since massive flooding in 2020. To keep water out, the UN maintained a complicated drainage and dike system. The UN was forced to abandon operations when the US cut funding, turning the camp “into an open sewer that helped spread cholera.” Starting in March, USAID staff repeatedly warned about the crisis conditions in the camp. (Some staff were kept on as the agency was being absorbed into the State Department.) Trump administration officials did not take action.
Nyariaka gave birth to a baby boy named Kuothethin, meaning “God is with us.” When she came back home from the hospital, “the new mom used the bathroom frequently, teetering back and forth to the overflowing latrines close to her house.” She soon began suffering from the intense vomiting and diarrhea that indicate cholera. Her husband carried her to the hospital, but she died just after they arrived. Their baby was just a few days old.
Reporting: Anna Maria Barry-Jester and Brett Murphy for ProPublica
Nyaweko
Like her mother Florence, who was a cleaner at a Kenyan clinic funded by the PEPFAR anti-AIDS initiative started by George W. Bush, Nyaweko had HIV. Nyaweko told her mother that if she died at least her mother wouldn’t have to worry about feeding her anymore. But when Nyaweko got pregnant, she realized she needed the drug that stops the transmission of HIV during childbirth. Four separate clinics told her they were out of it—when the USAID-funded record system many clinics used went down, clinics’ drug ordering systems went into chaos, and many began turning away new patients. The baby’s father said “she cannot give birth to a sick child because there is no medicine,” and Nyaweko fell into a deep depression.
Nyaweko died on May 1, 2025, her third suicide attempt. “All three suicide attempts happened after USAID stopped so suddenly with no warning or back-up plans. Florence believes if her daughter had the HIV meds she needed to keep herself and her baby healthy, she'd still be alive.”
Reporting: Ike Sriskandarajah for This American Life and Katharine Houreld for the Washington Post
Viola Kiden
A mother of three, 28-year-old Viola lived in a remote area of South Sudan. She was HIV-positive. USAID stopped supplying her antiretroviral drugs and she died soon after.
Reporting: Nicholas Kristof for the New York Times
Martha Juan
25-year-old Martha Juan stopped receiving antiretrovirals via USAID, according to Angelina Doki, a health volunteer who had worked with her. Angelina’s own supply of antiretrovirals was nearly depleted, and she feared she would die soon. Martha died first.
Reporting: Nicholas Kristof for the New York Times
Babagana Bukar Mohammed

Seven-year-old Babagana “was a cheerful boy who loved to ride his bike.” Babagana also had sickle cell disease, and he lived in a part of northeastern Nigeria that the extremist group Boko Haram has terrorized. When Babagana’s mother noticed he had a fever on February 2, 2025 she took him to a USAID-funded clinic where he had previously received care—but it had stopped operations a week earlier when the Trump administration ordered it to stop work. Babagana died that night. His doctor at the clinic said, “We are sure we would have done something to save the patient.”
Reporting: Gabrielle Emanuel and Jonathan Lambert for NPR
Lydia Nabirye

Despite an infant child who had just barely survived yellow fever and an ex-partner who had likely given her HIV before refusing to acknowledge their child, Lydia Nyabire still managed to laugh. The 28-year-old Ugandan’s charm drew customers in to the restaurant she ran with her mother. But when she learned that her son would never speak or walk, Lydia fell into a deep depression and began refusing her HIV medication.
A PEPFAR-funded nonprofit assigned Lydia a case worker to support her mental health and ensure she took her medicine. Regaining hope in the future, Lydia started taking her medicine again, and she aspired to become a nurse to treat others in the community. But then the Trump administration cancelled the program, forcing the case worker to stop visiting Lydia. Lydia stopped taking her medicine, and she died on March 26, 2025.
Reporting: Andrew Green for Devex and The Forsaken
Omran
The International Rescue Committee was scheduled to deliver US-funded medicines and medical supplies to a clinic near Khartoum, Sudan. A physician at the clinic thinks basic antibiotics “probably would have cured” the chest infection of 3-year-old Omran. But the International Rescue Committee project was thrown into chaos by USAID policy decisions. As Omran’s health deteriorated, his mom Islam al Mubarak Ibrahim carried him to 11 other health facilities, but none had the required medicine. Omran had been inseparable from his twin Marwan, and in the aftermath of Omran’s death, their mother couldn’t bring herself to tell Marwan that his brother was dead. She said, “One day, I will just tell him, ‘Your brother went to Paradise.’”
Reporting: Katharine Houreld and Hafiz Haroun for the Washington Post
Mohamat
In normal circumstances, nine-month-old Mohamat might have been diagnosed with malaria by a community health worker—USAID funded over 2,000 of them in northern Cameroon. By the time he made it to a health center after three days of burning fever, it had no injectable artesunate—USAID had funded that too. He died the same day. His father Alhadji Madou Goni said, “I feel so sad about my loss. I hope no one suffers from this again. Since there is hardship here, and people don’t have the means, we hope aid comes.”
Reporting: Amindeh Blaise Atabong, Robbie Corey-Boulet and Jennifer Rigby for Reuters
This is one of those posts where the “policy” label becomes a kind of moral evasion. When you abruptly interrupt food systems, HIV/TB/malaria treatment continuity, maternal–child health programs, and outbreak surveillance, the downstream isn’t abstract, but it’s excess mortality, concentrated among children and the medically vulnerable. Your decision to name individuals makes that causal chain impossible to hand-wave away. 
From a physician-scientist lens, what’s so chilling is how predictable the mechanisms are: medication stock-outs → rebound viremia/opportunistic infections; clinic closures → missed antenatal care and preventable neonatal deaths; disrupted vector control → malaria resurgence; weakened surveillance → delayed outbreak detection. None of this requires speculative theory, just basic biology plus supply chains. 
I also appreciate the discipline in your framing: debate the effectiveness of aid, sure, but don’t confuse “reform” with sudden withdrawal without transition. If a model estimates mortality at this scale, the exact point estimate matters less than the ethical fact that we knowingly pulled supports in a way that made deaths foreseeable. 
Thank you for writing the version that refuses anesthesia. Names should not be the price of attention, but in practice, they often are.
My god, what an indictment. Read it and weep.